Treating Androgenetic Alopecia In Women

Around one third of women experience hair loss (androgenetic alopecia) at some point in their lives. Among post-menopausal women, as many as two thirds suffer from hair loss or bald patches. Hair loss in women often has a greater impact than hair loss in men, because it is less socially accepted for them. Androgenetic alopecia can seriously affect a woman’s emotional wellbeing and quality of life.
The main type of hair loss in women is the same as in men. It is called androgenetic alopecia, or female (or male) pattern hair loss. In men, hair loss usually begins above the forehead, and the receding hairline eventually forms a characteristic “M” shape. Hair on top of the head also thins, often to the point of baldness. In women, androgenetic alopecia begins with gradual thinning at the part line, followed by increasingly diffuse hair loss radiating from the top of the head. A woman’s hairline rarely recedes, and women rarely go bald.
There are many possible causes of hair loss in women, including medical conditions, medications, and physical or emotional stress. If you notice unusual hair loss of any kind, it is important to consult your GP or a dermatologist to determine the cause and the right treatment. You can also ask your doctor for a referral to a therapist or support group to address emotional concerns. Hair loss in women can be frustrating, but in recent years there has been an increase in the resources available to tackle the problem.
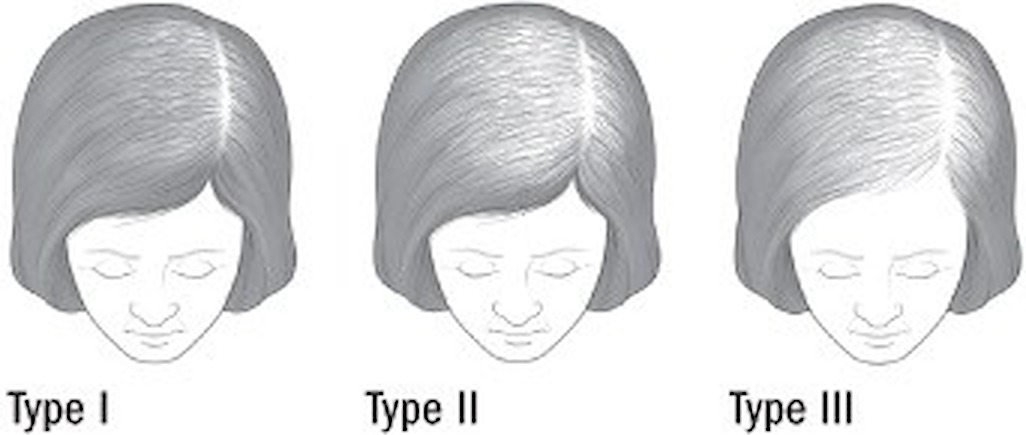
Almost every woman eventually develops some degree of hair loss. It can begin at any time after the onset of puberty, but women usually first notice it around the menopause, when hair loss typically increases. The risk rises with age and is higher for women with a family history of hair loss on either side.
As the name suggests, androgenetic alopecia involves the action of the hormones called androgens, which are essential for normal sexual development and have other important functions in both sexes, including sex drive and regulation of hair growth. The condition can be inherited and involves several genes. It can also be the result of an underlying endocrine disorder, such as overproduction of androgen or an androgen-secreting tumour on the ovary, pituitary gland or adrenal gland. In both cases, the alopecia is likely to be related to increased androgenic activity. But unlike androgenetic alopecia in men, in women the precise role of androgens is harder to determine. Given the possibility that an androgen-secreting tumour is involved, it is important to measure androgen levels in women with marked hair loss.
In both sexes, hair loss due to androgenetic alopecia occurs because of a genetically determined shortening of anagen, the growth phase of a hair, and a lengthening of the time between a hair being shed and the start of a new anagen phase. That means it takes longer for hair to start growing again after it has been shed in the course of the normal growth cycle. The hair follicle itself also changes, shrinking and producing a shorter, thinner hair shaft – a process known as “follicular miniaturisation”. As a result, thicker, pigmented, longer-lived “terminal” hairs are replaced by shorter, thinner, non-pigmented hairs called “vellus” hairs.
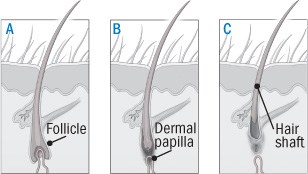
Every hair develops from a follicle – a narrow pocket in the skin – and goes through three phases of growth. Anagen (A), the active growth phase, lasts two to seven years. Catagen (B), the transitional phase, lasts about two weeks. During this phase the hair shaft moves up towards the surface of the skin and the dermal papilla (the structure that nourishes the cells that produce hair) begins to separate from the follicle. Telogen (C), the resting phase, lasts around three months, after which the hair is shed and a new hair begins to grow from the follicle.
A doctor diagnoses hair loss in women by taking a medical history and examining the scalp. They will observe the pattern of hair loss, check for signs of inflammation or infection, and may order blood tests to investigate other possible causes of hair loss, including hyperthyroidism, hypothyroidism and iron deficiency. Unless there are signs of excessive androgenic activity (such as irregular periods, acne and unwanted hair growth), a hormonal evaluation is usually not necessary.
Hair loss treatment for women
Medication is the most common treatment for hair loss in women. It includes the following:
Minoxidil (Rogaine, generic versions)
This medication was originally introduced as a treatment for high blood pressure, but people who used it noticed that they were growing hair in places where they had lost it. Research studies confirmed that minoxidil applied directly to the scalp could stimulate hair growth. As a result of those studies, the FDA originally approved over-the-counter 2% minoxidil to treat hair loss in women. Since then a 5% solution has also become available for when a stronger solution is needed for a woman’s hair loss.
Minoxidil is clearly not a miracle cure. Although it can produce new growth of fine hair in some – not all – women, it cannot restore the full density of the hair that has been lost. It is also not a quick fix for hair loss in women. You will not see results until you have used the medication for at least two months. The effect often peaks at around four months, but it can take longer, so plan for a trial period of six to twelve months. If minoxidil works for you, you need to keep using it to maintain those results. If you stop, you will lose hair again.
How to use minoxidil: make sure your hair and scalp are dry. Use the dropper or spray pump supplied with the over-the-counter solution and apply it twice a day to every area where your hair is thinning. Gently massage it into the scalp with your fingers so that it can reach the hair follicles. Then let your hair air-dry, wash your hands thoroughly, and wash off any solution that has dripped onto your forehead or face. Do not shampoo for at least four hours afterwards.
Some women find that the minoxidil solution leaves a deposit that dries out and irritates their scalp. This irritation, known as contact dermatitis, is probably not caused by the minoxidil itself, but rather by the alcohol included to help it dry.
Side effects and concerns: minoxidil is safe, but even apart from alcohol-related skin irritation it can have unpleasant side effects. Sometimes the new hair differs in colour and texture from the surrounding hair. Another risk is hypertrichosis – excessive hair growth in the wrong places, such as the cheeks or the forehead. (This problem is more likely with the stronger 5% solution.)
Because the patent on Rogaine (the brand-name version of minoxidil) has expired, many generic products are available. They all contain the same amount of minoxidil, but some contain additional ingredients, such as herbal extracts, which can cause allergic reactions.
Anti-androgens
Androgens include testosterone and other “male” hormones, which can accelerate hair loss in women. Some women who do not respond to minoxidil may benefit from the addition of the anti-androgen drug spironolactone (Aldactone) for the treatment of androgenetic alopecia. This is particularly true for women with polycystic ovary syndrome (PCOS), because they tend to produce excess androgens. Doctors usually prescribe spironolactone together with an oral contraceptive for women of childbearing age. (A woman taking either of these medicines should not become pregnant, because they can cause genital abnormalities in a male foetus.) Possible side effects include weight gain, loss of libido, depression and fatigue.
Iron supplements
Iron deficiency can be a cause of hair loss in some women. Your doctor can test the iron level in your blood, particularly if you are vegetarian, have a history of anaemia or have heavy menstrual bleeding. If you are iron deficient, you will need to take a supplement, and it may stop your hair loss. If your iron level is normal, however, taking extra iron will only cause side effects such as an upset stomach and constipation.
Hair transplant
Hair transplantation, a procedure that has been used in the United States since 1950 to treat androgenetic alopecia, involves removing a strip of scalp from the back of the head and using it to fill in a bald patch. Today, 90% of hair transplant surgeons use a technique called follicular unit transplantation, which was introduced in the mid-1990s.
During an FUE treatment we extract each graft individually from your scalp, without making a large incision as used to be done. Each graft is placed into a slit in the scalp created by a blade or needle in the area of missing hair. Hair grows this way naturally, in small clusters of one to four follicles, called follicular units. As a result, the transplant looks better than the larger “plugs” associated with the hair transplants of years gone by.
Discover More

Thinning Hair In Women
Hair loss is often seen as a male problem, yet it affects at least a third of women. Women usually experience thinning hair rather than going bald, and there are several possible underlying causes.
Read More
Hair Loss In Men
Male pattern baldness affects most men at some point in their lives. It usually takes 15 to 25 years to develop, it is difficult to predict, and it always follows a recognisable pattern.
Read More
Which Questions Should I Ask A Hair Transplant Clinic?
13 questions you should ask a hair transplant clinic before you commit to a treatment.
Read More